

Why prevention and early detection could save thousands of Filipino lives
PLUS:
- The Cancer Screening Guide Every Family Should Know
- Seven Warning Signs You Should Never Ignore
- HPV and Hepatitis B Vaccines: Protection Against Cancer
- The Truth About Cancer Blood Tests and Whole-Body Scans
- Cancer Without Financial Ruin: Where Filipinos Can Get Help
- Doctor’s Note: The Best Cancer Treatment May Begin Before Cancer Develops
CANCER BEFORE IT STRIKES
Why prevention and early detection could save thousands of Filipino lives

Cancer is one of the most feared words in medicine. For many families, hearing it immediately brings thoughts of chemotherapy, surgery, mounting hospital bills and uncertainty about the future.
But there is another side of the cancer story—one that deserves much greater attention.
Some cancers can be prevented before they develop. Others can be detected at an earlier, more treatable stage. And for many Filipinos, simple measures such as vaccination, smoking cessation and appropriate screening could make an enormous difference.
The challenge is ensuring that these opportunities reach people before cancer changes their lives.
By Rafael R. Castillo, MD
The diagnosis nobody wants to hear
Imagine a 52-year-old Filipino father sitting quietly across from his physician. For several months, he has noticed occasional blood in his stool. He assumes it is hemorrhoids.
He is busy at work. His children are still in school. His aging parents need financial assistance. Besides, the bleeding comes and goes. Why worry?
Eventually, the bleeding becomes more frequent. He develops fatigue and unintentionally loses weight. A colonoscopy reveals a tumor. The biopsy confirms colorectal cancer.
His first question is predictable.
“Doc, will I survive?”
His second is equally understandable.
“How much will treatment cost?”
Now imagine a different scenario. At age 45, he discusses colorectal cancer screening with his physician. A screening colonoscopy detects a precancerous polyp, which is removed before it develops into cancer.
No chemotherapy. No major cancer surgery. No months of uncertainty.
For that particular lesion, cancer was prevented before it had the opportunity to develop.
This is one of the most powerful promises of cancer prevention: sometimes the best cancer treatment is the treatment we never need.
The example is illustrative, but the medical principle is firmly established.
Cancer is not always a matter of bad luck
Cancer develops when cells acquire changes that allow them to grow and divide abnormally, evade normal regulatory mechanisms and sometimes invade surrounding tissues or spread elsewhere.
These changes can arise from inherited susceptibility, aging, environmental exposures, infections, lifestyle-related factors and biological processes beyond our control.
Consequently, even people who live very healthy lives can develop cancer. That is important to remember. A cancer diagnosis should never become an occasion to blame patients for their illness. Nevertheless, a substantial proportion of cancers worldwide is associated with potentially modifiable risk factors.
The World Health Organization identifies tobacco use, alcohol consumption, unhealthy diets, physical inactivity, excess body weight, certain infections and environmental exposures among important contributors to cancer risk.
The International Agency for Research on Cancer and WHO have estimated that roughly four in ten new cancer cases globally may be attributable to preventable causes, although the proportion varies by country, cancer type and the factors included in the analysis.
The message is not that cancer can always be avoided.
It is that prevention deserves a much larger place in our national response to cancer.
For decades, cancer discussions have understandably focused on chemotherapy, surgery, radiotherapy and increasingly sophisticated treatments.
These advances have saved lives. But preventing cancer and diagnosing it earlier can also spare patients suffering, disability and enormous financial costs.
The three levels of cancer prevention
Cancer prevention is often misunderstood as a single activity. In reality, it involves three complementary approaches.
1. Primary prevention: Stop cancer before it develops
Primary prevention reduces exposure to factors that cause or contribute to cancer.
Examples include avoiding tobacco, receiving HPV and hepatitis B vaccinations, limiting or avoiding alcohol, maintaining a healthy weight, staying physically active and protecting oneself from excessive ultraviolet radiation.
Some preventive measures are particularly effective because they target a known cause of cancer. For example, persistent infection with certain high-risk human papillomavirus types is responsible for nearly all cervical cancers. Vaccination against HPV can prevent infections responsible for many of these cancers.
Similarly, chronic hepatitis B infection increases the risk of liver cancer. Hepatitis B vaccination therefore offers long-term protection against an important cancer risk factor.
These vaccines represent one of medicine’s remarkable achievements: immunization that can prevent certain cancers decades later.
2. Secondary prevention: Detect cancer or precancerous disease early
Secondary prevention involves identifying disease before symptoms appear, when treatment may be more effective. However, screening should not be confused with indiscriminate testing. Effective screening requires evidence that testing a defined population produces more benefit than harm.
Some tests can detect precancerous changes. Others identify cancers at earlier stages.
For example:
- Cervical screening can detect precancerous abnormalities.
- Colorectal screening can detect cancer and, with some methods, precancerous polyps.
- Mammography can detect breast cancers before they become clinically apparent.
- Low-dose CT can reduce lung-cancer mortality in appropriately selected high-risk individuals.
But not every cancer has an effective screening test. And screening can produce false positives, unnecessary procedures, overdiagnosis and anxiety.
More testing is not automatically better healthcare.
3. Tertiary prevention: Reduce complications and recurrence
Once cancer has been diagnosed, tertiary prevention aims to reduce complications, improve quality of life and, where possible, lower the risk of recurrence or subsequent cancers.
It includes evidence-based treatment, rehabilitation, management of treatment-related complications, smoking cessation, appropriate survivorship care and recommended follow-up.
These three approaches should work together.
A comprehensive cancer program must prevent disease where possible, detect appropriate cancers early and provide timely, effective treatment when cancer occurs.
The cancers we have a real opportunity to prevent
Lung cancer: The enormous price of tobacco
Tobacco smoking remains one of the most important preventable causes of cancer.
Although lung cancer can occur in people who have never smoked, smoking accounts for a large proportion of cases.
Tobacco also contributes to cancers of the mouth, throat, esophagus, bladder, pancreas, kidney and several other organs.
The most effective preventive measure is straightforward: Do not start smoking. If you smoke, quitting remains worthwhile at any age.
Stopping smoking reduces future cancer risk, although the degree of risk reduction depends on smoking history and time since cessation. Avoiding secondhand smoke is also important.
Vaping should not be promoted as harmless. Its long-term cancer risks are not yet fully characterized, and non-smokers—especially young people—should not begin using nicotine products.
For selected adults with substantial smoking histories, annual low-dose CT screening can reduce lung-cancer mortality. But this is not a recommendation for everyone.
The widely used US Preventive Services Task Force criteria recommend annual low-dose CT for adults aged 50–80 with at least a 20-pack-year smoking history who currently smoke or quit within the past 15 years, provided they remain candidates for potentially curative treatment.
Philippine implementation should account for local guidelines, access, cost and appropriate shared decision-making.
A routine chest X-ray is not an equivalent substitute for evidence-based lung-cancer screening.
Cervical cancer: A cancer we could dramatically reduce
Cervical cancer is especially important because its principal cause is well understood. Persistent infection with high-risk HPV types causes nearly all cervical cancers.
The disease often develops gradually, creating opportunities for vaccination and detection of precancerous lesions.
HPV vaccination is most effective before exposure to the virus. WHO recommends vaccination of girls aged 9–14 as a primary target population, with vaccination schedules depending on age, immune status and national policy.
Screening remains important even for vaccinated women because vaccination does not eliminate every cervical-cancer risk.
WHO recommends HPV DNA testing as the preferred screening method where feasible, with screening generally beginning at age 30 in the general population and earlier for women living with HIV.
The Philippine screening pathway should follow current DOH guidance and available services.
The tragedy is that cervical cancer remains a major cause of illness and death despite the availability of effective preventive interventions. The challenge is no longer simply scientific discovery. It is implementation.
Liver cancer: Preventing the infection that can cause it
Chronic hepatitis B infection is a major risk factor for hepatocellular carcinoma. The Philippines has long faced a substantial burden of hepatitis B. Vaccination, including timely birth-dose vaccination, is a cornerstone of prevention.
Other important measures include preventing hepatitis transmission, diagnosing chronic hepatitis B and C, providing appropriate antiviral treatment and addressing alcohol-related and metabolic liver disease.
People with cirrhosis and selected patients with chronic hepatitis B may require liver-cancer surveillance under specialist guidance. Surveillance is different from population-wide screening. Routine liver ultrasound or alpha-fetoprotein testing is not recommended for every healthy adult. The goal is to identify those whose underlying risk justifies surveillance.
Colorectal cancer: Sometimes a polyp is the warning
Colorectal cancer provides a particularly compelling example of prevention through screening. Many colorectal cancers develop from precancerous polyps over time. Colonoscopy can detect and remove these lesions.
Stool-based screening tests can also identify people who require further evaluation. For average-risk adults, several major international guidelines recommend beginning screening at age 45, although Philippine recommendations and practical screening choices should be considered.
Screening may need to begin earlier in people with a strong family history, hereditary cancer syndromes or certain medical conditions.
A positive stool-based screening test requires timely diagnostic colonoscopy. And an important distinction must be emphasized: Rectal bleeding, unexplained iron-deficiency anemia, persistent changes in bowel habits or unexplained weight loss require medical assessment—not routine screening. A patient with symptoms needs diagnostic evaluation regardless of age.
Breast cancer: The value—and limitations—of early detection
October is Breast Cancer Awareness Month, making this an especially timely subject. Breast cancer is among the most frequently diagnosed cancers in Filipino women.
Mammography can detect some breast cancers before symptoms develop and has been shown to reduce breast-cancer mortality in appropriately selected populations. However, recommendations differ regarding the age to begin screening and screening intervals. The USPSTF recommends biennial mammography for women aged 40–74 at average risk. Other professional organizations recommend different starting ages or intervals.
For Filipino women, decisions should consider local guidance, personal risk, breast density, access and informed preferences. Women with strong family histories or suspected hereditary predisposition may require individualized risk assessment and potentially additional imaging.
Breast awareness remains valuable. A new breast lump, nipple discharge—especially bloody discharge—skin dimpling or other persistent breast changes should prompt medical evaluation.
But breast self-examination alone is not a proven substitute for recommended screening.
The lifestyle choices that matter
Cancer prevention does not require a mysterious formula. It involves familiar health behaviors practiced consistently.
Avoid tobacco
Smoking cessation is among the most effective actions a smoker can take to reduce future cancer risk.
Limit or avoid alcohol
Alcohol is a recognized carcinogen. For cancer prevention, less alcohol generally means less risk; abstaining avoids alcohol-related cancer exposure.
Maintain a healthy weight
Excess body fat is associated with increased risks of several cancers, including colorectal, endometrial and postmenopausal breast cancer.
Move regularly
Physical activity contributes to overall health and is associated with lower risks of certain cancers.
Adults should generally aim for 150–300 minutes of moderate-intensity aerobic activity weekly, or an equivalent amount of vigorous activity, plus muscle-strengthening activities.
Eat a balanced diet
Emphasize vegetables, fruits, whole grains and legumes.
Limit processed meat, excessive red meat and highly processed foods that displace nutritious choices. No single food prevents cancer.
Get recommended vaccinations
HPV and hepatitis B vaccination are important cancer-prevention interventions.
Protect yourself from excessive sun exposure
Use shade, appropriate clothing and sunscreen when indicated.
Know your family history
A strong family history can change screening recommendations.
Seek medical attention for persistent symptoms
Early diagnosis is not limited to formal screening programs.
Recognizing concerning symptoms and obtaining timely evaluation can also improve outcomes.
Why Filipinos still miss the opportunity
If cancer prevention is so important, why do many people fail to receive appropriate preventive care? The answer is rarely simple.
Some are unaware that screening exists. Others fear discovering cancer. Some cannot afford testing. Others live far from facilities offering screening and treatment. Still others postpone care because work, family responsibilities and daily survival take priority.
There are also structural problems. A screening test is of limited value if a positive result is not followed by timely diagnostic confirmation and treatment.
A cervical screening program cannot succeed if women with abnormal results cannot obtain colposcopy or treatment.
A positive stool test cannot prevent colorectal cancer if colonoscopy is inaccessible.
A suspicious mammogram offers little benefit if diagnostic imaging, biopsy and treatment are delayed.
This is why cancer prevention must be organized as a complete patient pathway, not merely a collection of isolated tests.
The Philippines needs a prevention-first cancer strategy
The National Integrated Cancer Control Act provides a framework for improving cancer prevention, care and survivorship. But implementation must reach communities.
A stronger national strategy should prioritize:
- Expanding HPV and hepatitis B vaccination.
- Improving access to evidence-based cancer screening.
- Strengthening primary-care recognition of warning symptoms.
- Ensuring timely diagnostic confirmation after abnormal screening.
- Improving access to treatment and financial protection.
- Establishing measurable targets for vaccination, screening, diagnostic follow-up and treatment outcomes.
Health education should be culturally appropriate, affordable and accessible.
Cancer prevention must reach the market vendor, farmer, factory worker, office employee, teacher and retiree—not only people who can afford annual executive checkups.
The promise of prevention should not become another privilege reserved for the wealthy.
The future we can change
Cancer will remain part of medicine for the foreseeable future. We cannot prevent every malignancy. We cannot guarantee that screening will detect every cancer. And we must never suggest that people who develop cancer failed to take proper care of themselves. But there is substantial room for progress.
A teenager vaccinated against HPV. A newborn protected against hepatitis B. A smoker who finally quits. A woman who receives appropriate cervical screening. A father whose precancerous colon polyp is removed. A patient whose persistent symptoms are investigated promptly.
Each represents an opportunity to change the course of a life.
The future of cancer care should not be measured only by how effectively we treat cancer after it develops. It should also be measured by how many cancers we prevent—and how many lives we protect through timely diagnosis.
That is the promise of cancer prevention.
And it is a promise worth bringing to every Filipino family.
“The most remarkable cancer treatment may be the one a patient never needs—because prevention worked.”
THE CANCER SCREENING GUIDE EVERY FILIPINO FAMILY SHOULD KNOW
What to screen for, when to begin and why more tests are not always better

Cancer screening can save lives, but only when the right tests are performed in the right people.
The following guide summarizes commonly used evidence-based recommendations. These are not substitutes for Philippine national guidelines or individualized medical advice.
| Cancer | Who may benefit | Common evidence-based approach |
| Breast | Average-risk women aged 40–74 | Mammography every two years under USPSTF recommendations; other guidelines differ |
| Cervical | Women generally beginning at age 30 under WHO population guidance | HPV DNA testing preferred where available; interval depends on national program and test |
| Colorectal | Average-risk adults aged 45–75 | Stool-based tests or direct visualization, including colonoscopy |
| Lung | Selected adults aged 50–80 with substantial smoking history | Annual low-dose CT under specified eligibility criteria |
| Prostate | Selected men after individualized discussion | PSA testing based on age, risk and preferences; not automatic universal screening |
| Liver | Selected high-risk patients, including some with cirrhosis or chronic hepatitis B | Specialist-directed surveillance, often ultrasound at defined intervals |
Important: People with concerning symptoms need diagnostic assessment, not screening. Those with strong family histories, hereditary syndromes or other risk factors may need earlier or different evaluation.
The screening mistake to avoid
A common misconception is that a comprehensive annual cancer blood panel or whole-body scan is automatically the best approach.
It is not.
The best screening strategy is evidence-based, risk-appropriate and connected to timely diagnostic follow-up.
SEVEN CANCER WARNING SIGNS YOU SHOULD NEVER IGNORE
Symptoms that deserve attention—not panic
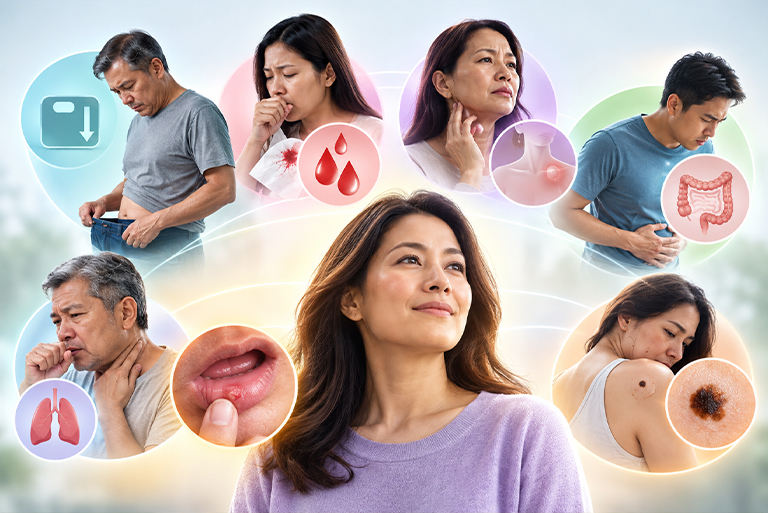
Most symptoms associated with cancer have noncancerous explanations.
Nevertheless, persistent or unexplained changes should not be dismissed.
1. Unexplained weight loss
Losing weight without trying, particularly when accompanied by fatigue or other symptoms, warrants evaluation.
2. Unusual bleeding
Blood in the stool or urine, coughing blood, postmenopausal bleeding and unexplained persistent bleeding require assessment.
3. A new or enlarging lump
A persistent breast, neck, testicular or other unexplained lump should be examined.
4. Persistent changes in bowel or bladder habits
New, persistent changes in bowel movements or urination may require investigation.
5. A sore or lesion that does not heal
Persistent mouth ulcers, skin lesions or wounds warrant attention.
6. Persistent cough, hoarseness or swallowing difficulty
Symptoms that do not resolve as expected should be evaluated, especially in people with additional risk factors.
7. A changing mole or unusual skin lesion
Changes in size, shape, color or appearance deserve medical assessment.
Remember
These symptoms do not necessarily mean cancer.
But persistent or unexplained symptoms deserve professional evaluation.
Early diagnosis begins when warning signs are taken seriously.
TWO VACCINES THAT CAN HELP PREVENT CANCER
How HPV and hepatitis B vaccination protect future generations

Vaccines are usually associated with preventing infectious diseases.
But two important vaccines also help prevent cancers.
HPV vaccine
Persistent infection with certain HPV types causes nearly all cervical cancers and contributes to several other cancers, including some anal, penile, vulvar, vaginal and oropharyngeal cancers.
Vaccination before exposure provides the greatest preventive benefit.
WHO identifies girls aged 9–14 as the primary target group for cervical-cancer prevention.
The exact number of doses depends on age, immune status and national policy.
Vaccination does not eliminate the need for recommended cervical screening.
Hepatitis B vaccine
Chronic hepatitis B infection is a major cause of liver cancer.
Preventing hepatitis B infection therefore reduces future liver-cancer risk.
Timely birth-dose vaccination, followed by completion of the recommended vaccine series, is particularly important.
Adults who remain susceptible may also benefit from vaccination according to applicable recommendations.
The long-term perspective
A vaccine given during childhood can help prevent a cancer that might otherwise develop decades later.
That makes vaccination one of the most forward-looking investments in public health.
THE TRUTH ABOUT CANCER BLOOD TESTS AND WHOLE-BODY SCANS
Why more screening is not always better screening

The promise is attractive. One blood test. One scan. Dozens of cancers detected before symptoms develop. Unfortunately, medical science is more complicated.
Multi-cancer early-detection blood tests are being studied, but evidence that routine use reduces cancer mortality in the general population remains insufficient.
False-positive findings can trigger anxiety, additional imaging and invasive procedures. False-negative results may provide false reassurance.
Similarly, whole-body CT or MRI screening of asymptomatic average-risk adults is not generally recommended as a routine cancer-screening strategy.
CT exposes patients to ionizing radiation. MRI avoids ionizing radiation but may reveal incidental findings that require further evaluation. Neither approach has established itself as a replacement for proven population-based screening.
What about tumor markers?
Tumor markers such as CEA, CA-125 and CA 19-9 have important uses in selected clinical settings. But they are generally not appropriate as routine cancer-screening tests for healthy, average-risk individuals.
A normal result does not rule out cancer. An elevated result does not necessarily mean cancer.
The right test for the right person is more valuable than the largest number of tests.
CANCER WITHOUT FINANCIAL RUIN
Where Filipino patients can begin looking for assistance

A cancer diagnosis may create substantial financial strain even when patients have PhilHealth coverage. Families should explore available assistance early rather than waiting until bills become overwhelming. Potential sources include:
PhilHealth: Applicable benefit packages, including relevant cancer-related benefits and case rates.
Department of Health: The Cancer Assistance Fund and other programs, subject to current eligibility, appropriations and participating facilities.
Medical Assistance to Indigent and Financially Incapacitated Patients (MAIFIP): Assistance subject to program rules, facility participation and available funds.
Malasakit Centers: One-stop assistance arrangements at participating hospitals.
PCSO: Medical assistance programs, subject to prevailing requirements and availability.
DSWD and local government units: Financial and social assistance for eligible patients.
Practical patient checklist
Before treatment begins, ask the hospital social worker or financial counselor:
- Which PhilHealth benefits apply to my diagnosis and planned treatment?
- Is the hospital accredited for the relevant package?
- Which expenses are excluded?
- Can I apply for assistance before admission or treatment?
- What medical abstracts, quotations and identification documents are required?
- Is there a patient navigator or social worker who can help coordinate applications?
Life Hacks
TEN WAYS TO LOWER YOUR CANCER RISK
Practical steps for everyday life

1. Make your home smoke-free. Avoid smoking and secondhand smoke.
2. Avoid alcohol when possible. Less alcohol generally means lower alcohol-related cancer risk.
3. Move every day. Combine regular aerobic activity with strength training.
4. Maintain a healthy weight. Focus on sustainable habits rather than extreme dieting.
5. Eat more plant foods. Include vegetables, fruits, whole grains and legumes.
6. Limit processed meat. Choose varied protein sources and avoid making processed meats a daily staple.
7. Get recommended vaccines. Check HPV and hepatitis B vaccination eligibility.
8. Protect your skin. Reduce excessive ultraviolet exposure.
9. Know your family history. Tell your physician about cancers among close relatives, especially diagnoses at young ages.
10. Follow evidence-based screening recommendations. Do not ignore symptoms or substitute unproven tests for established screening.
Remember: Healthy living reduces risk; it does not guarantee that cancer will never develop.
PUBLIC-HEALTH COMMENTARY
WHY THE PHILIPPINES MUST INVEST MORE IN CANCER PREVENTION
From treating advanced disease to preventing avoidable suffering

The Philippines needs a cancer strategy that reaches beyond hospitals. Treatment is essential. But a system that focuses predominantly on treating advanced cancer will remain financially and clinically burdened.
A stronger prevention-first approach requires investments in vaccination, tobacco control, healthy food environments, primary care, evidence-based screening and prompt diagnostic services. It also requires a functioning referral system.
Consider cervical cancer. Vaccination can reduce future disease risk. HPV screening can detect high-risk infection. Follow-up can identify precancerous lesions. Treatment of those lesions can prevent progression. But if any link in that pathway fails, the patient may still develop cancer.
The same principle applies to colorectal cancer screening. A positive stool test must lead to colonoscopy. A suspicious breast lesion must lead to timely imaging and biopsy.
A patient with symptoms must not wait months for diagnostic evaluation.
The challenge is not simply offering more tests. It is completing the journey from prevention to diagnosis and treatment.
This is where Universal Health Care and cancer control must intersect. Primary-care systems should identify eligible patients and coordinate preventive services.
PhilHealth and other financing mechanisms should support evidence-based care.
Local governments should help ensure that disadvantaged communities can access vaccination and screening.
Hospitals should provide timely diagnostic confirmation and treatment.
And public-health authorities should measure not only how many people were screened, but how many abnormal results received appropriate follow-up.
A successful cancer-control program should ultimately reduce preventable illness, avoidable deaths, treatment delays and catastrophic household spending.
That is how prevention becomes more than a slogan.
REFERENCES
- World Health Organization. Cancer fact sheet. Overview of cancer burden, risk factors, prevention and early detection.
WHO cancer fact sheet - International Agency for Research on Cancer. Global Cancer Observatory, GLOBOCAN 2022. Country-specific cancer incidence and mortality estimates, including the Philippines.
IARC Global Cancer Observatory - World Health Organization. Global strategy to accelerate the elimination of cervical cancer as a public health problem. 2020.
WHO cervical cancer elimination strategy - World Health Organization. WHO guideline for screening and treatment of cervical pre-cancer lesions for cervical cancer prevention. Second edition. 2021.
WHO cervical screening guidance - US Preventive Services Task Force. Breast Cancer: Screening. Final recommendation statement. 2024.
USPSTF breast cancer screening - US Preventive Services Task Force. Colorectal Cancer: Screening. Final recommendation statement. 2021.
USPSTF colorectal cancer screening - US Preventive Services Task Force. Lung Cancer: Screening. Final recommendation statement. 2021.
USPSTF lung cancer screening - World Cancer Research Fund/American Institute for Cancer Research. Diet, Nutrition, Physical Activity and Cancer: A Global Perspective. Third Expert Report.
WCRF cancer prevention recommendations - World Health Organization. Guidelines on physical activity and sedentary behaviour. 2020.
WHO physical activity guidelines - Republic Act No. 11215. National Integrated Cancer Control Act. Philippines, 2019.
National Integrated Cancer Control Act - Republic Act No. 11223. Universal Health Care Act. Philippines, 2019.
Universal Health Care Act









Leave a Reply